We May Not Understand Control Groups
active placebo, clinical trials, control group effects, placebo effect, side effects
It’s well known that randomized trials are some of the most efficient ways to make causal inferences and to determine how much something (an intervention) differs from the comparator (some sort of control). Random assignment helps make these goals easier by minimizing selection bias and making the distribution of prognostic factors between groups random (not balanced).1
Discussions (similar to the one above) praising the efficiency of randomized trials are widespread, however, few of these discussions take a close look at some of the common assumptions that individuals hold regarding randomized trials. And unfortunately, these common assumptions may be based on outdated evidence and simplistic ideas.
The Placebo Effect Isn’t What We Often Think
For example, in placebo-controlled trials, many individuals make the assumption that much of the improvement seen in the control group over time is due to the placebo effect, as modeled by the graph below.

However, inquiries into this topic have yielded contradictory results, in that the placebo effect may not be as powerful as we assume.
One systematic review2 that looked at 130 clinical trials concluded the following,
“We found little evidence in general that placebos had powerful clinical effects. Although placebos had no significant effects on objective or binary outcomes, they had possible small benefits in studies with continuous subjective outcomes and for the treatment of pain. Outside the setting of clinical trials, there is no justification for the use of placebos.”
Thus, the placebo effect had some small effects in areas where it is difficult to objectively measure a phenomenon and where there is a higher likelihood for encountering measurement error. However, measurement error is not the only thing that could explain some of the improvements seen in control groups, which we often attribute to the placebo effect.
We simply need to reread two sections of a paper by the very anesthesiologist who popularized the placebo effect3 and who claimed that it had the ability to put patients’ conditions into remission.
Here, Henry Beecher (the anesthesiologist) claims that placebo effects are powerful:
“It is evident that placebos have a high degree of therapeutic effectiveness in treating subjective responses, decided improvement, interpreted under the unknowns technique as a real therapeutic effect, being produced in 35.2 ± 2.2% of cases….
Placebos have not only remarkable therapeutic power but also toxic effects. These are both subjective and objective. The reaction (psychological) component of suffering has power to produce gross physical change.”
Then he reports another observation from his patients.
“The evidence is that placebos are most effective when the stress is greatest.”
If you measured someone’s stress (let’s say objectively, via cortisol measurements) and they were extremely stressed and if you followed up after a certain period of time, it would be very likely that the next measurement of their stress (cortisol levels) would be less than the first measurement.
A slightly reverse situation would likely apply too: if you measured someone’s happiness (in some theoretical objective way) and they were extremely happy, it’s very likely that their next measurement of happiness would not be so high. This phenomenon is known as regression to the mean,4 and it can explain why many individuals who are in an abnormal state, feel slightly more normal over time.
We can see this displayed below in the graph of simulated blood pressure data5 where the change in blood pressure is predicted by baseline blood pressure. The individuals with higher blood pressure at baseline experienced a larger decrease in blood pressure over time.

This could possibly explain why Beecher observed that placebo was most effective for situations in which stress was the greatest.
It may not have been just the patients’ minds that led to remission of symptoms, rather the combination of regressing towards an average from a more extreme value, the placebo effect, along with the subjectivity and measurement error of the instruments may have led to this phenomenon of experiencing relief as a function of time.6
This isn’t to say that placebo effects are nonexistent or that they’re not relevant, they still are because they serve as controls for various other phenomena that come along with them. For example, it seems very unlikely that in a clinical trial that recruits healthy participants and aims to improve their intelligence with an experimental drug, that regression to the mean could explain the improvements seen in the control group.
In a trial aiming to improve biomarkers in healthy participants, could regression towards the mean or noise explain all the variance we see in the control group? Probably not. It seems very feasible that the placebo effect can result in changes to both subjective and objective outcomes, irrespective of the effects of regression to the mean and measurement error, however, I’m inclined to believe that many of the claims regarding the placebo effect may be exaggerated.
Thus, a more accurate way to think of control group effects would be to incorporate phenomena such as regression to the mean, the placebo effect, and other factors, as shown below.

Of course, the proportion of these individual effects would likely vary depending on the scenario(s). Here, the proportions of effects in the control group reflect my beliefs about what contributes to improvements seen in sick individuals who are followed over time.
While the model above is certainly an improvement over the first bar graph in the article all the way above, it too may also be simplistic… and may even be wrong.7 I’ll first discuss some theoretical examples and then present some evidence.
The Additive Model Is Too Simple
If we add up all the possible effects that lead to improvements in the control group, such as regression to the mean, the placebo effect, measurement error, unspecific effects etc, we can call this giant block (the blue block) the “total control group effect”, at least for the sake of this discussion. This is shown in the bar graph below. Notice that it has a total effect of 6.

Again, here we are assuming that all the possible things that lead to improvements in the control group are represented by the blue bar. Thus, we design a clinical trial with the assumption that the total control group effect, AKA that represented by the blue bar, will also be the same in the treatment group. This is the “Additive Model” because it simply adds the treatment effect (red bar) on top of the control effect (blue bar), giving a total effect of 10. We subtract the total effect of the treatment group (10) from the total control group effect (6) to get:
Treatment-specific effect (4) = Total treatment group effect (10) - Total control group effect (6)
Therefore, we estimate that the drug has an effect of 4 whereas all the effects that contribute to the control result in an effect of 6. In the form of a linear model, we would model this as y = constant + b(group), where b is the difference between the treatment group and the control group, and group would be coded as 0 or 1, etc.
This idea may be too simplistic as it assumes that the control effect (the blue bar) will be constant between groups.
However, several studies have shown disparities in placebo/control effects between groups, with placebo/control effects sometimes being larger in control groups than in treatment groups.8–10
Experimental studies have also found that the sum of the drug effect and the placebo effect is often larger than the total treatment effect.11, 12 This doesn’t seem to support the additive model, where we assume the total control effect is constant in both groups.
It doesn’t take into account that there may be an interaction13, 14 that occurs between the control group effects and the treatment effects, especially if there are possible factors that could lead the participants in the clinical trial to discover that they’ve been allocated to the treatment group.
Thus, a more inclusive model of these possible factors, in the form of a linear model, would be:
y = *constant + βgroup + βinteractio**n(s) + ϵ*

These interactions could result in many scenarios, but let’s look at two simple ones.
If a participant in a drug trial is aware of the side effects of the drug beforehand, and receives the drug and experiences side effects, he/she may now have some confirmation that they’ve received the actual intervention, and may overestimate their improvement in a subjective outcome and/or may experience placebo/physiological mechanisms that overlap and interact, thus amplifying the control effects. The overall treatment group effect would increase. This would be a synergistic interaction14, as shown below. Notice the control group has a total effect of 6, while the drug group has a total effect of 13.

Now let’s say in another scenario, a patient in a drug trial was unaware of the possible side effects of the drug and experienced some side effects, which has somehow convinced the participant that they may not improve, or the physiological interaction in the mechanisms between the drug and placebo result in negative outcomes. This may lead to a reduction in the placebo effect and a reduction in other unspecific control effects. This would be an antagonistic interaction14, as shown below. It’s reduced the overall treatment group effect from 13 to 8.

Thus, when we design clinical trials with comparators, we’re often assuming that the treatment-specific effect can be estimated by taking the difference between the total treatment group effect and the total control group effect, because we assume the control effect is constant between groups. But again, as shown above, this may be far too simplistic.
Possible Directions
So what’s the solution? How can we design clinical trials to better account for these possible interactions between the intervention and the control group effects? A potential solution that’s been put forth by several researchers over the years is the balanced-placebo design.7, 11, 12, 15, 16 The balanced-placebo design is essentially a 2 x 2 factorial design where two groups will receive the drug and two groups will receive placebo.
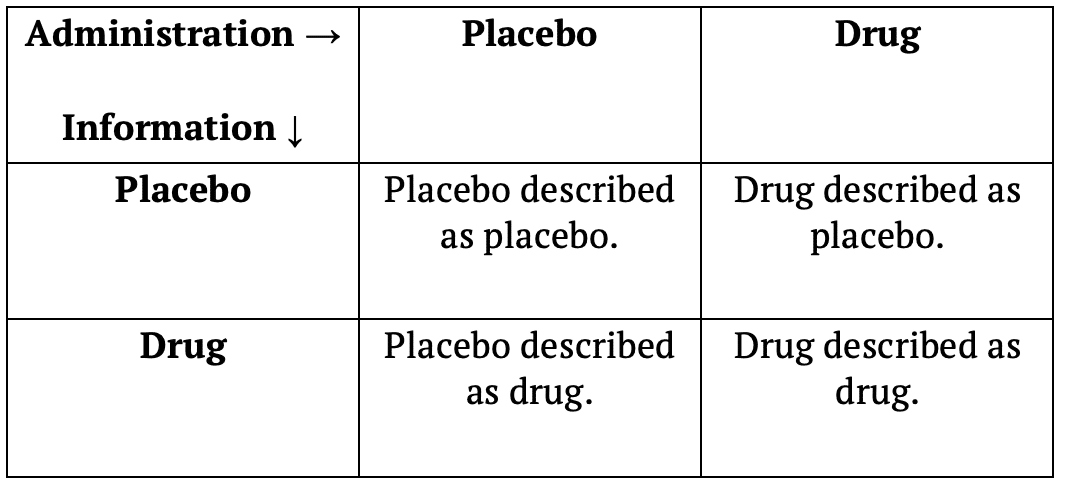
Out of the two groups receiving the drug, one will be told that they’re receiving placebo, while the other is told they’re receiving the drug. The same would apply to the two groups receiving the placebo. One will be told that they’re receiving the placebo, while the other is told they’re receiving the drug. While this design may account for interactions between control group effects and the intervention, I can’t say I’m much of a fan of it as it requires more groups (therefore more participants) and doesn’t use blinding. It may also be unethical.
A very simple solution to me (out of several proposed designs) is the use of an “active placebo.”7 Active placebos are substances that don’t yield any beneficial effects, but are designed to mimic some of the side effects of the intervention (pretty sure a more appropriate term for them would be nocebo). Thus, controlling for the possible interaction(s) that could occur if the participant is affected by the side effects of the intervention. This will make it harder for the participant to know whether they got the intervention or the placebo.
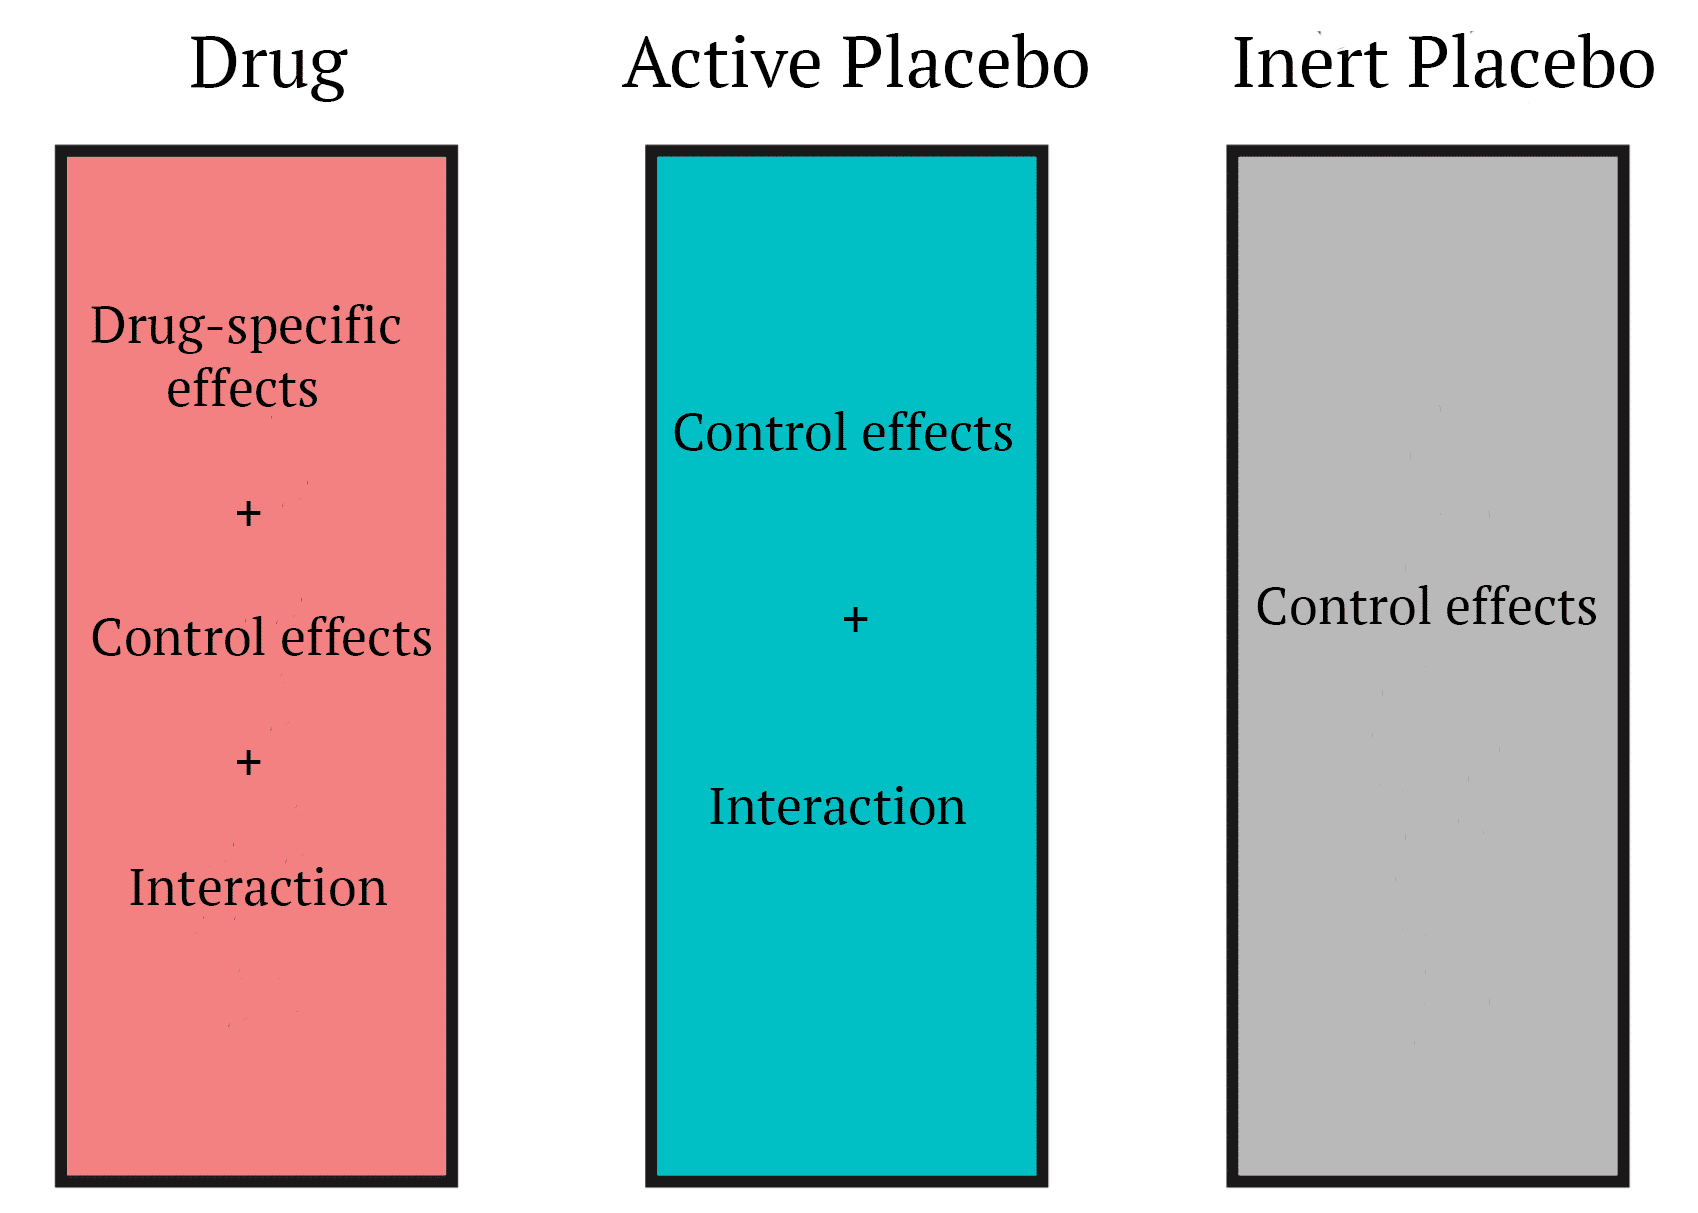
Psychiatrist Scott Alexander of Slate Star Codex and LessWrong is skeptical of active placebos and believes that the research doesn’t support their usage.17 In his article about selective serotonin reuptake inhibitors he writes,
“In other words, active placebo research has fallen out of favor in the modern world. Most studies that used active placebo are very old studies that were not very well conducted. Those studies failed to find an active-placebo-vs.-drug difference because they weren’t good enough to do this. But they also failed to find an active-placebo-vs.-inactive-placebo difference. So they provide no support for the idea that active placebos are stronger than inactive placebos in depression and in fact somewhat weigh against it.”
Scott uses a narrative review from 200017 that looked at previous active-placebo trials to support this perspective, but several other studies that have used active placebos have been carried out since
- Several of these are of much higher quality than the studies discussed in the review he cites. A more recent methodological review,18 published by one of the authors who systematically searched the literature to find that placebo effects were underwhelming in trials with objective outcomes,2 concludes the following,
Pharmacological active placebo control interventions are rarely used in randomized clinical trials, but they constitute a methodological tool which merits serious consideration. We suggest that active placebos are used more often in trials of drugs with noticeable side effects, especially in situations where the expected therapeutic effects are modest and the risk of bias due to unblinding is high.
Luckily, active placebo research doesn’t seem to have fallen out of favor. Is active placebo research the solution to the problems mentioned above? I’m not sure. There are several other proposed designs that attempt to account for possible interactions that can occur and they may be more practical or less biased. It seems like recognizing that such interactions could occur in the first place would be the first step towards finding a solution.
Acknowledgements: I’d like to thank Andrew Vigotsky for bringing my attention to several of the pieces cited in this article and for offering comments on an early version of this piece.
References
References
Abstract
BACKGROUND: Placebo treatments have been reported to help patients with many diseases, but the quality of the evidence supporting this finding has not been rigorously evaluated. METHODS: We conducted a systematic review of clinical trials in which patients were randomly assigned to either placebo or no treatment. A placebo could be pharmacologic (e.g., a tablet), physical (e.g., a manipulation), or psychological (e.g., a conversation). RESULTS: We identified 130 trials that met our inclusion criteria. After the exclusion of 16 trials without relevant data on outcomes, there were 32 with binary outcomes (involving 3795 patients, with a median of 51 patients per trial) and 82 with continuous outcomes (involving 4730 patients, with a median of 27 patients per trial). As compared with no treatment, placebo had no significant effect on binary outcomes (pooled relative risk of an unwanted outcome with placebo, 0.95; 95 percent confidence interval, 0.88 to 1.02), regardless of whether these outcomes were subjective or objective …
Abstract
Placebos have doubtless been used for centuries by wise physicians as well as by quacks, but it is only recently that recognition of an enquiring kind has been given the clinical circumstance where the use of this tool is essential "... to distinguish pharmacological effects from the effects of suggestion, and... to obtain an unbiased assessment of the result of experiment." It is interesting that Pepper could say as recently as 10 years ago "apparently there has never been a paper published discussing [primarily] the important subject of the placebo." In 1953 Gaddum1said: Such tablets are sometimes called placebos, but it is better to call them dummies. According to the Shorter Oxford Dictionary the word placebo has been used since 1811 to mean a medicine given more to please than to benefit the patient. Dummy tablets are not particularly noted for the pleasure which they give to their recipients.
Abstract
Galton founded many concepts in statistics, among them correlation, quartile, and percentile. Here Stephen Senn examines one of Galton's most important statistical legacies ? one that is at once so trivial that it is blindingly obvious, and so deep that many scientists spend their whole career being fooled by it.
Abstract
NEW FINDINGS: What is the topic of this review? In 'personalized medicine', various plots and analyses are purported to quantify individual differences in intervention response, identify responders/non-responders and explore response moderators or mediators. What advances does it highlight? We highlight the impact of within-subject random variation, which is inevitable even with 'gold-standard' measurement tools/protocols and sometimes so substantial that it explains all apparent individual response differences. True individual response differences are quantified only by comparing the SDs of changes between intervention and comparator arms. When these SDs are similar, true individual response differences are clinically unimportant and further analysis unwarranted. Within the 'hot topic' of personalized medicine, we scrutinize common approaches for presenting and quantifying individual differences in the physiological response to an intervention. First, we explain how popular plots used to present individual differences in response are contaminated by random within-subject variation and the regression to the mean artefact …
Abstract
Statistical regression to the mean predicts that patients selected for abnormalcy will, on the average, tend to improve. We argue that most improvements attributed to the placebo effect are actually instances of statistical regression. First, whereas older clinical trials susceptible to regression resulted in a marked improvement in placebo-treated patients, in a modern series of clinical trials whose design tended to protect against regression, we found no significant improvement (median change 0$$3 per cent, p $>$ 0$$05) in placebo-treated patients. Secondly, regression can yield sizeable improvements, even among biochemical tests. Among a series of 15 biochemical tests, theoretical estimates of the improvement due to regression by selection of patients as high abnormals (i.e. 3 standard deviations above the mean) ranged from 2$$5 per cent for serum sodium to 26 per cent for serum lactate dehydrogenase (median 10 per cent); empirical estimates ranged from 3$$8 per cent for serum chloride to 37$$3 per cent for serum phosphorus (median 9$$5 per cent) …
Abstract
Double-blinded randomized clinical trials (RCTs) assume that pharmacological interventions have drug-specific and unspecific components. Traditional RCTs postulate an additivity of these two components. In this review, we provide evidence from both clinical trials and experimental studies that questions this 'additive model'. Given that the evaluation of drug treatments in RCTs is based on the assumption of additivity, its violation has far-reaching consequences. Therefore, we discuss an interactive model that, in contrast to the additive model, considers interactions between placebo and drug-specific effects. Moreover, we discuss implications for future clinical trials and present novel study designs enabling researchers to consider the complex interplay of drug-specific and unspecific effects.
Abstract
Randomized, double-blind, placebo-controlled trials on neuropathic pain treatment are accumulating, so an updated review of the available evidence is needed. Studies were identified using MEDLINE and EMBASE searches. Numbers needed to treat (NNT) and numbers needed to harm (NNH) values were used to compare the efficacy and safety of different treatments for a number of neuropathic pain conditions. One hundred and seventy-four studies were included, representing a 66\% increase in published randomized, placebo-controlled trials in the last 5 years. Painful poly-neuropathy (most often due to diabetes) was examined in 69 studies, postherpetic neuralgia in 23, while peripheral nerve injury, central pain, HIV neuropathy, and trigeminal neuralgia were less often studied. Tricyclic antidepressants, serotonin noradrenaline reuptake inhibitors, the anticonvulsants gabapentin and pregabalin, and opioids are the drug classes for which there is the best evidence for a clinical relevant effect. Despite a 66\% increase in published trials only a limited improvement of neuropathic pain treatment has been obtained …
Abstract
BACKGROUND: New drug treatments, clinical trials, and standards of quality for assessment of evidence justify an update of evidence-based recommendations for the pharmacological treatment of neuropathic pain. Using the Grading of Recommendations Assessment, Development, and Evaluation (GRADE), we revised the Special Interest Group on Neuropathic Pain (NeuPSIG) recommendations for the pharmacotherapy of neuropathic pain based on the results of a systematic review and meta-analysis. METHODS: Between April, 2013, and January, 2014, NeuPSIG of the International Association for the Study of Pain did a systematic review and meta-analysis of randomised, double-blind studies of oral and topical pharmacotherapy for neuropathic pain, including studies published in peer-reviewed journals since January, 1966, and unpublished trials retrieved from ClinicalTrials.gov and websites of pharmaceutical companies. We used number needed to treat (NNT) for 50\% pain relief as a primary measure and assessed publication bias; NNT was calculated with the fixed-effects Mantel-Haenszel method. FINDINGS: 229 studies were included in the meta-analysis …
Abstract
OBJECTIVE: This meta-analysis investigated how the supportive care provided in antidepressant clinical trials for late-life depression influences response and drop-out rates. METHODS: Medline, PsycINFO, and PubMed were searched to identify trials contrasting antidepressants with placebo or active comparator in outpatients aged at least 60 years with major depressive disorder. Hierarchical linear modeling was used to determine whether treatment assignment (medication versus placebo), study type (placebo-controlled or comparator), study duration, and the number of study visits affected response and attrition rates. RESULTS: In the response rate analysis, a significant interaction was found between study visits and treatment assignment (odds ratio [OR]: 0.89, t = -2.186, df = 36, p = 0.035), such that each additional visit over the grand mean for the sample increased average placebo response by 2.5\% while not significantly affecting medication response. Controlling for other variables, the effect of this interaction was to dramatically decrease average medication versus placebo differences in trials having greater numbers of study visits …
Abstract
BACKGROUND: The total effect of a medication is the sum of its drug effect, placebo effect (meaning response), and their possible interaction. Current interpretation of clinical trials' results assumes no interaction. Demonstrating such an interaction has been difficult due to lack of an appropriate study design. METHODS: 180 adults were randomized to caffeine (300 mg) or placebo groups. Each group received the assigned intervention described by the investigators as caffeine or placebo, in a randomized crossover design. 4-hour-area-under-the-curve of energy, sleepiness, nausea (on 100 mm visual analog scales), and systolic blood pressure levels as well as caffeine pharmacokinetics (in 22 volunteers nested in the caffeine group) were determined. Caffeine drug, placebo, placebo-plus-interaction, and total effects were estimated by comparing outcomes after, receiving caffeine described as placebo to receiving placebo described as placebo, receiving placebo described as caffeine or placebo, receiving caffeine described as caffeine or placebo, and receiving caffeine described as caffeine to receiving placebo described as placebo, respectively …
Abstract
BACKGROUND: It is an inherent assumption in randomised controlled trials that the drug effect can be estimated by subtracting the response during placebo from the response during active drug treatment. OBJECTIVE: To test the assumption of additivity. The primary hypothesis was that the total treatment effect is smaller than the sum of the drug effect and the placebo effect. The secondary hypothesis was that non-additivity was most pronounced in participants with large placebo effects. METHODS: We used a within-subject randomised blinded balanced placebo design and included 48 healthy volunteers (50\% males), mean (SD) age 23.4 (6.2) years. Experimental pain was induced by injections of hypertonic saline into the masseter muscle. Participants received four injections with hypertonic saline along with lidocaine or matching placebo in randomised order: A: received hypertonic saline/told hypertonic saline; B: received hypertonic saline+lidocaine/told hypertonic saline; C: received hypertonic saline+placebo/told hypertonic saline+pain killer; D: received hypertonic saline+lidocaine/told hypertonic saline+pain killer …
Abstract
We revisited the three interrelated epidemiological concepts of effect modification, interaction and mediation for clinical investigators and examined their applicability when using research databases. The standard methods that are available to assess interaction, effect modification and mediation are explained and exemplified. For each concept, we first give a simple “best-case” example from a randomized controlled trial, followed by a structurally similar example from an observational study using research databases. Our explanation of the examples is based on recent theoretical developments and insights in the context of large health care databases. Terminology is sometimes ambiguous for what constitutes effect modification and interaction. The strong assumptions underlying the assessment of interaction, and particularly mediation, require clinicians and epidemiologists to take extra care when conducting observational studies in the context of health care databases. These strong assumptions may limit the applicability of interaction and mediation assessments, at least until the biases and limitations of these assessments when using large research databases are clarified.
Abstract
KENNETH J. ROTHMAN; SYNERGY AND ANTAGONISM IN CAUSE-EFFECT RELATIONSHIPS1, American Journal of Epidemiology, Volume 99, Issue 6, 1 June 1974, Pages 385–388, htt
Abstract
Placebo treatments and opiate drugs are thought to have common effects on the opioid system and pain-related brain processes. This has created excitement about the potential for expectations to modulate drug effects themselves. If drug effects differ as a function of belief, this would challenge the assumptions underlying the standard clinical trial. We conducted two studies to directly examine the relationship between expectations and opioid analgesia. We administered the opioid agonist remifentanil to human subjects during experimental thermal pain and manipulated participants' knowledge of drug delivery using an open-hidden design. This allowed us to test drug effects, expectancy (knowledge) effects, and their interactions on pain reports and pain-related responses in the brain. Remifentanil and expectancy both reduced pain, but drug effects on pain reports and fMRI activity did not interact with expectancy. Regions associated with pain processing showed drug-induced modulation during both Open and Hidden conditions, with no differences in drug effects as a function of expectation …
Abstract
We investigated the effect of a possible interaction between topical analgesic treatment and treatment expectation on pain at the behavioral and neuronal level by combining topical lidocaine/prilocaine treatment with an expectancy manipulation in a 2 by 2 within-subject design (open treatment, hidden treatment, placebo, control). Thirty-two healthy subjects received heat pain stimuli on capsaicin-pretreated skin and rated their experienced pain during functional magnetic resonance imaging. This allowed us to separate drug- and expectancy-related effects at the behavioral and neuronal levels and to test whether they interact during the processing of painful stimuli. Pain ratings were reduced during active treatment and were associated with reduced activity in the anterior insular cortex. Pain ratings were lower in open treatment compared with hidden treatment and were related to reduced activity in the anterior insular cortex, the anterior cingulate cortex, the secondary somatosensory cortex, and the thalamus …
Abstract
OBJECTIVE: Recent reports have criticized the design of antidepressant studies and have questioned their validity. These critics have concluded that antidepressants are no better than placebo treatment and that their illusory superiority depends on methodologically flawed studies and biased clinical evaluations. It has been suggested that the blind in randomized trials is penetrable-since clinician's guesses exceed chance-and that only active placebo can appropriately camouflage the difference between drug and placebo response. Furthermore, evidence has been cited to suggest that psychotherapy is as effective as antidepressants in both the acute and maintenance treatment of depression. These positions are often accepted as valid and have been broadly discussed in both the lay press and scientific literature. The purpose of this review is to reassess the cited data that support these assertions. METHOD: The authors examined the specific studies that were cited in these reports, evaluated their methodology, and conducted aggregate analyses …
Abstract
OBJECTIVES: Active placebos are control interventions that mimic the side effects of the experimental interventions in randomized trials and are sometimes used to reduce the risk of unblinding. We wanted to assess how often randomized clinical drug trials use active placebo control groups; to provide a catalog, and a characterization, of such trials; and to analyze methodological arguments for and against the use of active placebo. STUDY DESIGN AND SETTING: An overview consisting of three thematically linked substudies. In an observational substudy, we assessed the prevalence of active placebo groups based on a random sample of 200 PubMed indexed placebo-controlled randomized drug trials published in October 2013. In a systematic review, we identified and characterized trials with active placebo control groups irrespective of publication time. In a third substudy, we reviewed publications with substantial methodological comments on active placebo groups (searches in PubMed, The Cochrane Library, Google Scholar, and HighWirePress). RESULTS: The prevalence of trials with active placebo groups published in 2013 was 1 out of 200 (95\% confidence interval: 0-2), 0.5\% (0-1\%) …
Linked from (5)
- All Posts
- Blog § All Posts
- How Did We Figure Out Smoking Causes Lung Cancer? …better or worseand if the effects can be ruled out by the placebo or nocebo effect, or through phenomena like regression towards the mean
- Site Map § Search & Navigation
- Statistics § Latest Statistics Articles
Comments